
Upstream Digestion
Published by Upstream Digestion
Upstream DigestionA personal exploration of digestion, pressure, food processing and a simple question: could some problems begin much further upstream than we think?
Digestion is a long process. What eventually reaches the large intestine has already passed through the stomach, pancreas, liver and small intestine.
When symptoms appear downstream, it is natural to concentrate on where those symptoms are being felt. But that raises another question: what was happening earlier in the digestive process?
This website explores a hypothesis rather than presenting a proven medical theory.
The idea is that digestion may sometimes be better understood as an interconnected system. Food composition, digestive secretions, intestinal contents, gas, volume and movement may influence what happens further along the digestive tract.
The purpose of Upstream Digestion is to ask questions, document observations and encourage careful scientific investigation.
This project began with years of personal digestive problems and an attempt to understand why conventional explanations did not seem to explain everything I was experiencing.
Over time I began thinking about digestion less like a collection of separate organs and more like a processing system — almost like an engine or refinery — where what happens at the beginning can affect everything that follows.
That led to one recurring question:
Personal experience can generate interesting questions, but it cannot establish whether a medical hypothesis is correct.
This section will develop as scientific papers, established digestive physiology and evidence relevant to the upstream hypothesis are collected and examined.
Evidence that challenges the hypothesis is just as important as evidence that might support it.
Creative expressions of upstream and downstream digestion are welcome — including supportive, critical, humorous and challenging viewpoints.
Gallery images are published for discussion and exploration. Contributor material represents the contributor's own expression and is not medical advice or scientific proof.
Published by Upstream Digestion
Upstream Digestion
Published by Upstream Digestion
Upstream Digestion
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution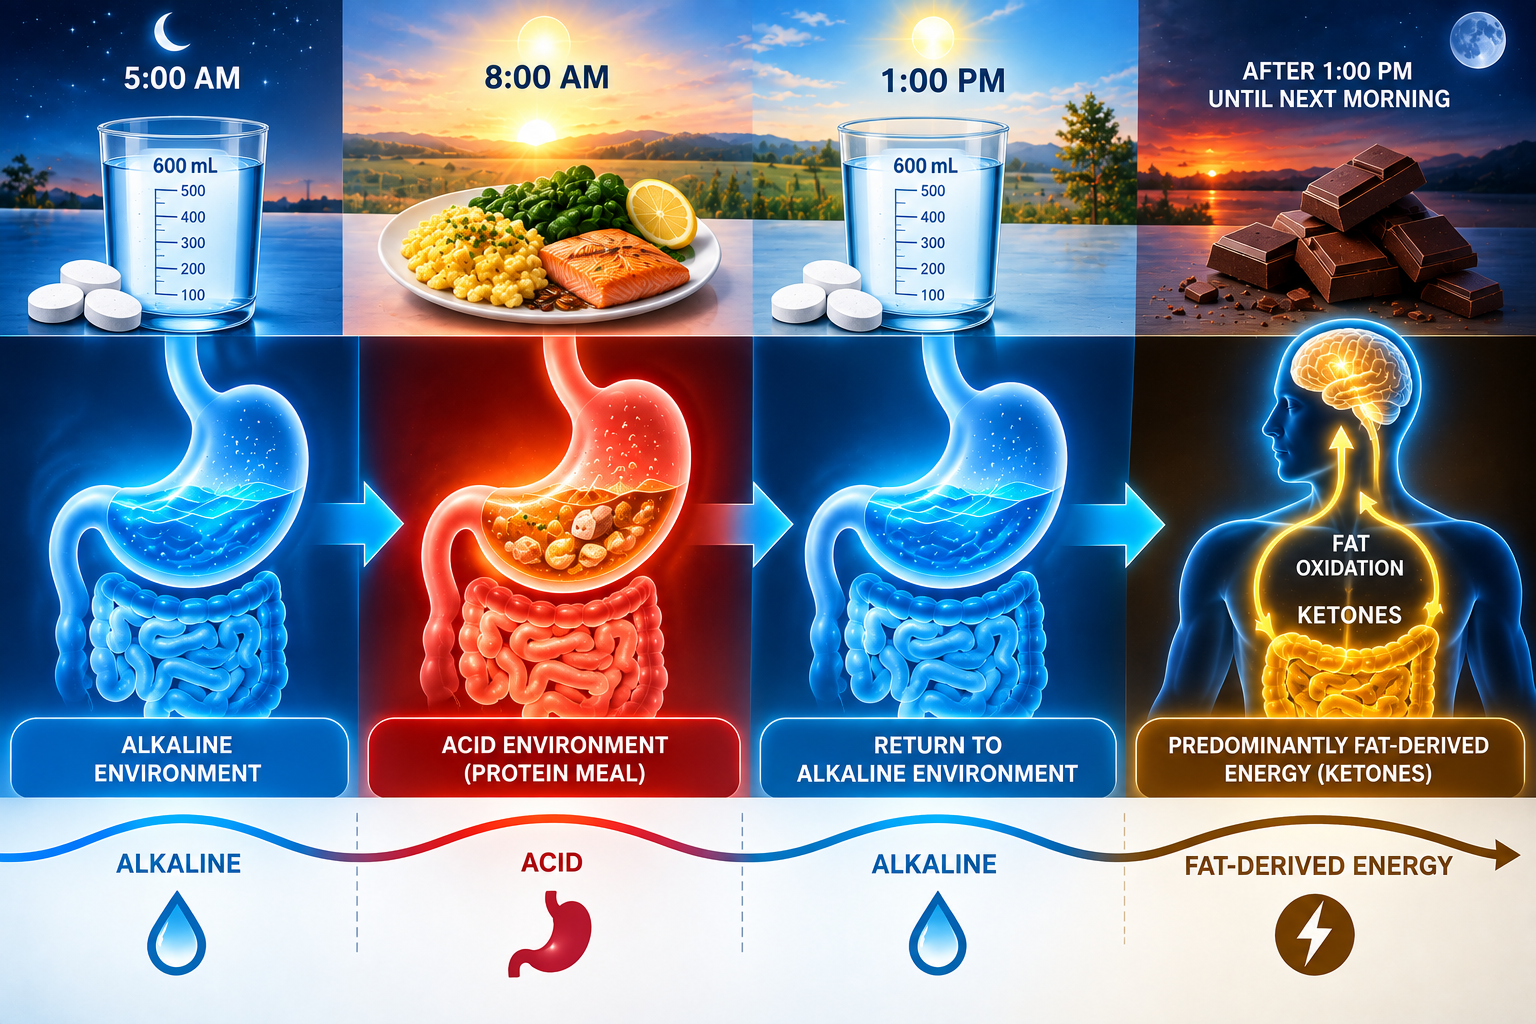
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution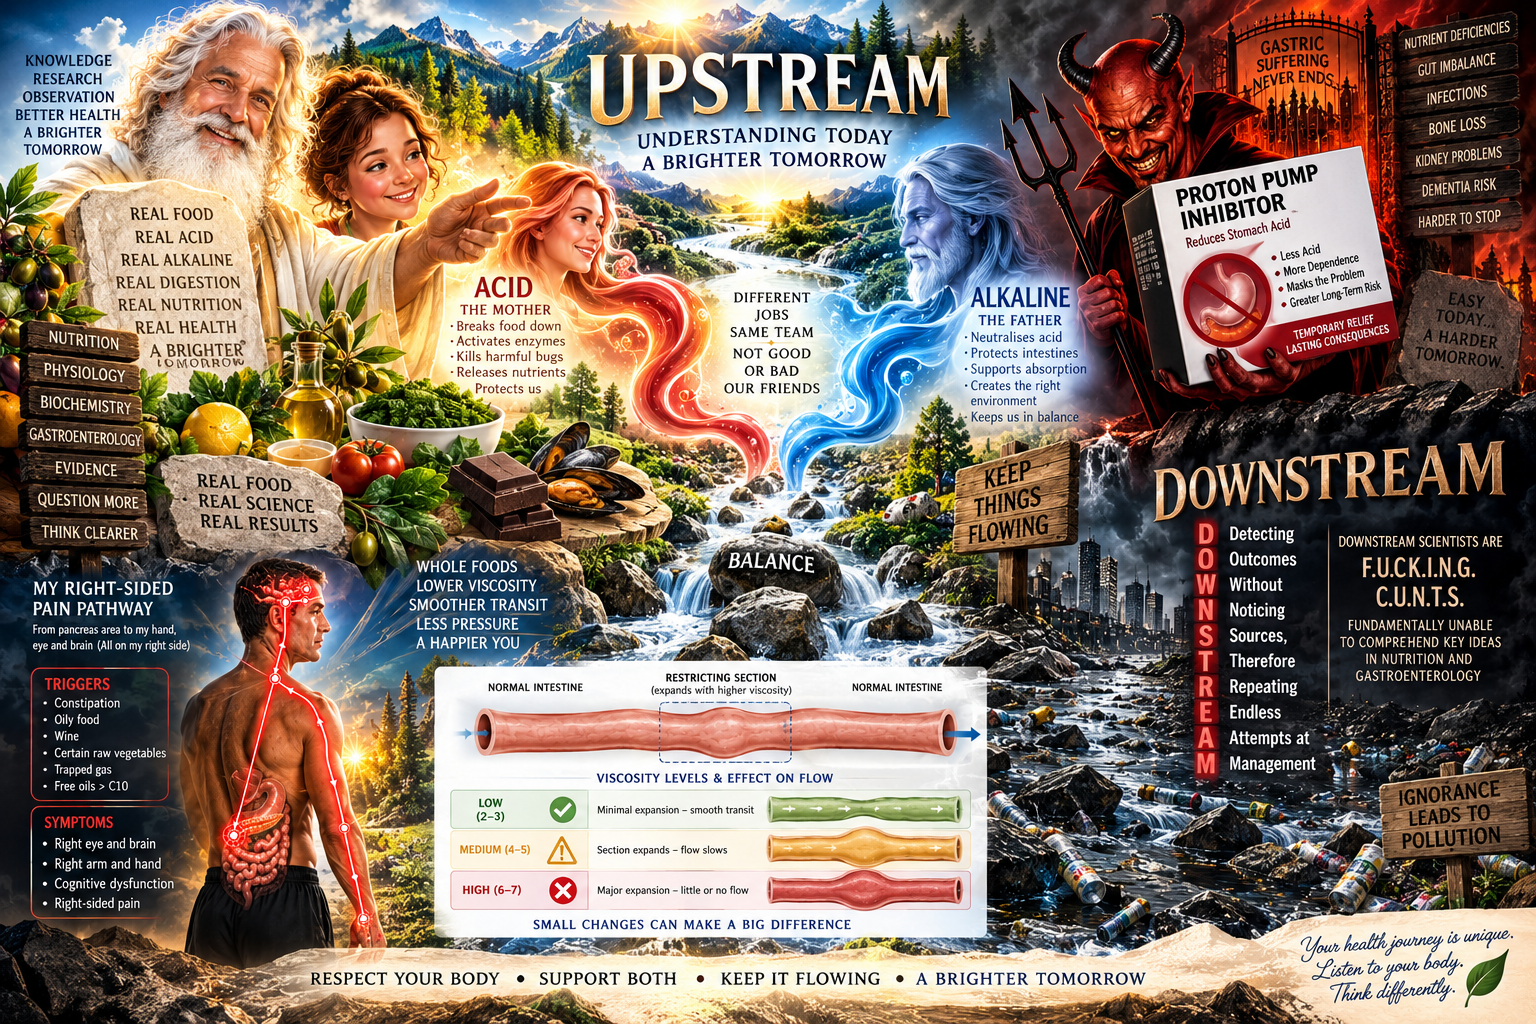
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by Tony
Community contribution
Submitted by TONY
Community contribution
Submitted by TONY
Community contributionStep 1 of 2: Verify your email below. After you click the verification link in your email, Step 2 opens automatically and shows the photo selector.
The photo chooser is deliberately shown only after email verification, so there is no image field on this first screen. Your email address is kept private and is never printed in the public gallery.
Every submitted image goes into a private moderation queue. Nothing becomes public automatically.
If email verification has not yet been connected, the gallery will remain safely closed to public uploads until that setup is completed.
Have you tried looking at your digestive problems differently? Have you noticed something that researchers or other visitors might find interesting?
Community Forum — Enter ForumShare what happened to you.
This forum is for people to share their own real-life experiences with food, digestion, mood, depression, cognitive function and general wellbeing.
Our primary interest is ordinary whole foods and naturally occurring food ingredients. Vitamin, mineral and other supplement recommendations are not the focus of this forum.
When posting, please tell us:
This is a place for sharing personal experiences. It is not a medical advice forum.
By participating, you agree that you will not diagnose another person, prescribe a treatment, or tell another person to start, stop or change medication.
You must not present a personal experience as proof that something will prevent, treat or cure depression, cognitive impairment or any other medical condition.
Discussion of your own experience with vitamins, minerals or supplements may be permitted, but please keep the focus on whole foods. Do not encourage another person to take a supplement or to exceed the manufacturer's directions on the product label.
If you have a medical condition, take medication, are pregnant, or are considering a significant dietary change, seek appropriate professional medical advice.
Posts represent individual experiences and opinions and are not medical advice.
Tony
https://youtu.be/2GBuBdRVSnY?si=bLQxXKlRNjJqpRUy
Tony
⚠️ CRITICAL SAFETY NOTICE — READ BEFORE INTERPRETING ANY OF THESE POSTS
THIS EXPERIMENT IS EVOLVING IN REAL TIME.
The quantities, timing and interpretations recorded throughout these posts reflect what I was doing at the time each observation was made. They should not be regarded as a fixed protocol.
Later updates in this notice supersede earlier quantities. I will not continually rewrite the historical record as the experiment evolves.
My current use of Quick-Eze has increased to 8 tablets per day — 4 tablets per alkaline cycle.
The manufacturer’s labelled maximum is 12 tablets per day, but that does not mean my current repeated use is appropriate or safe for another person. Eight tablets represents a substantial ongoing calcium- and magnesium-containing antacid load.
I AM DOCUMENTING THIS FOR SCIENTIFIC OBSERVATION. I AM NOT RECOMMENDING THAT THE GENERAL PUBLIC REPRODUCE IT.
My blood-pressure readings are now consistently approximately 120–130 mmHg systolic and 70–80 mmHg diastolic. I have not personally experienced readings consistently in this range since I was a very young man.
That is an observation, not proof that this experiment caused the change.
⚠️ THE CLEAR BREAK BETWEEN PHASES IS CRITICAL
After doing this for a considerable period, one potential danger is particularly obvious to me:
THE ALKALINE AND ACID PHASES MUST NOT BE ALLOWED TO RUN INTO ONE ANOTHER.
My final alkaline phase occurs at approximately 5:00 am. I deliberately allow a clear interval before eating the subsequent meal containing additional citric acid.
Taking calcium- and magnesium-containing antacids too close to that meal could raise gastric pH when an acidic gastric environment is required for normal digestion. If material from the preceding phase has not adequately cleared, the interaction becomes even less predictable.
For that reason, I regard inadequate separation between phases as a potentially serious problem.
ALKALINE → CLEAR BREAK → ACID/MEAL → CLEAR BREAK → ALKALINE
THE BREAK IS NOT OPTIONAL WITHIN MY EXPERIMENTAL MODEL.
It is fundamental to what I am investigating.
This website is a real-time record of a personal experiment, not a finished protocol. What I am doing tomorrow may not be identical to what I am doing today.
Do not take an isolated quantity or timing from an earlier post and assume it represents my current practice.
The purpose of publishing this material is to place the observations before people capable of investigating them properly—not to provide the public with instructions for reproducing the experiment.
Tony
Recap
https://youtu.be/dLS2u6ModJw?si=EqyFpR05Igi6TTzp
Tony
Must see
https://youtu.be/XBtPJ8r9xFc?si=SmvfVtO0Awmmnqqr
Tony
POST 1 OF 4
1. History of structural digestive abnormality
Surgery occurred around three years ago after what Tony believes was a chronically twisted intestine. Surgery corrected the twisting itself.
Tony believes residual structural consequences remain. He believes the duodenum and adjoining area are extremely dilated and that at least one section narrows significantly.
Laxatives and conventional diets have not adequately compensated in his experience.
2. Right-sided symptom phenomenon
Tony estimates he has described the phenomenon to at least 50 doctors.
It is most noticeable when constipated after eating. He experiences an unusual sensation affecting the right side of the body. Subjectively, it feels as though something travels through the right arm, towards the right eye and then the right side of the head.
He explicitly does not claim that material literally travels by that route. The biological mechanism is unknown.
The important observation is the consistency of its association with digestive conditions.
3. Possible relationship with gluconeogenesis
Tony suspects the right-sided phenomenon may occur during a metabolic state in which gluconeogenesis becomes especially relevant.
This remains a hypothesis rather than an established mechanism.
4. Reason for restricting protein
Protein is not eliminated.
The aim is to provide approximately what is needed for essential structure, repair and biological functions.
Tony tries to avoid routinely supplying a large excess that could potentially become substrate for glucose production.
He emphasises that this decision is based on his abnormal digestive system and should not automatically be applied to someone with normal anatomy and metabolism.
5. How citric acid entered the experiment
Citric acid was originally investigated to improve digestion and transit, not neurological disease.
Tony noticed what he perceived as a dramatic reduction in transit viscosity. Digestion also appeared more efficient subjectively.
He gradually increased the quantity over time. For more than six months he used approximately 80–100 g per day during a two-meal regimen.
These are described as personal experimental quantities, not recommended or established safe doses.
6. Observations during high citric-acid exposure
Tony reported improvements in mental clarity, cleaner skin and general wellbeing.
He eventually concluded that eating two substantial meals daily was unsustainable.
This became the foundation of the acid–alkaline cycle.
7. Reconsidering protein as an energy source
Protein is essential for muscle, repair, amino acids and other biological functions.
Tony questioned whether protein needs to provide much of the body’s energy.
Morning food became focused on protein and micronutrition. Later energy provision became more fat-based.
Chocolate became part of that later energy phase.
8. Discovery of separate acid and alkaline phases
Citric acid appeared useful with the morning meal.
Chocolate appeared not to require citric acid, and Tony felt chocolate digested better during the later alkaline phase.
This led to two deliberately separated periods: a morning acid cycle associated with the protein-rich meal, and a later alkaline cycle associated with chocolate and fat-derived energy.
9. Homemade chocolate mousse with MCT
Tony now makes a chocolate mousse containing MCT oil.
The icing sugar in the mousse provides carbohydrate that is digested and absorbed as glucose. MCT oil can be rapidly metabolised by the liver and contribute to ketone production.
Glucose and ketone bodies can both provide energy to the brain.
The aim is to make both energy substrates available during the alkaline phase. The intention is to reduce reliance on additional glucose production through gluconeogenesis.
Tony is not claiming that the brain consciously selects one fuel over another. Normal physiology determines how the available fuels are used.
Tony reports that this latest variation has worked very well subjectively.
10. MCT during the acid phase
A smaller amount of MCT is also present during the acid phase.
The intention is to preserve some ability to generate ketones throughout both phases.
Digestive environments are separated while potential brain-energy supply remains more continuous.
The biological importance remains unproven.
11. Evolution of the theory
The theory is no longer only about separating protein digestion from fat-derived energy.
It now also concerns coordination of digestive timing, food composition, glucose availability, ketone availability, protein processing and energy utilisation.
12. Neurological-type symptoms
Tony reports previously having many symptoms resembling features associated with Alzheimer’s and Parkinson’s.
He reports these symptoms disappeared during development of the regimen.
This does not prove that he had either disease. It does not establish that citric acid, acid/alkaline cycling, altered fuels or another component caused the improvement.
The observation prompted the larger upstream-versus-downstream hypothesis.
13. Blood-pressure observation
Diastolic pressure had recently been around 106 mmHg.
Later readings became consistently lower, including below 80 mmHg.
Tony does not claim the digestive protocol caused this. Blood pressure can vary for many reasons.
The size and timing of the change became an important personal trigger to speak publicly.
He views repeated potentially important observations as creating a responsibility to investigate and report them.
14. Blood-test observation
Recent pathology results reportedly improved markedly compared with previous results.
This is an objective personal observation.
It cannot establish citric acid as the cause. Diet, metabolism, hydration, medication, supplementation and other physiological factors could contribute.
15. Claim regarding a possible bypass pathway
After three years of observation and experimentation, Tony believes he may have identified a pathway capable of bypassing what he calls the “mainstream” forms of Alzheimer’s and Parkinson’s.
By mainstream he means cases without an established hereditary, mechanical or other clearly identified cause.
This is presented as a hypothesis requiring investigation, not proof.
16. First core principle: reduce viscosity
Dramatically reduce intestinal-transit viscosity and maintain that reduction consistently for a prolonged period.
The objective is not merely laxation or bowel stimulation.
The physical characteristics of intestinal contents are considered fundamental, especially when the intestine is narrowed, dilated or compromised.
17. Second core principle: control protein presentation
The particular concern is protein rather than all nutrients.
Protein should travel in a slippery, viscosity-stabilised environment.
The focus is not only how much protein is eaten, but its physical presentation and processing.
The hypothesis is that slower, more stable presentation may allow digestion, absorption and metabolism to occur more orderly.
This is considered especially relevant when amino acids are being used metabolically and gluconeogenesis is active.
18. Protein metabolism, nitrogen handling and uric acid
Amino-acid metabolism can involve deamination. Nitrogen removed from amino acids must be handled safely.
The urea cycle is a major pathway for converting potentially toxic ammonia into urea for excretion.
Uric acid, or urate, is a separate nitrogen-containing waste product produced mainly from the breakdown of purines rather than directly through the urea cycle.
Uric acid is primarily cleared from the body through the kidneys, with some elimination through the intestine.
Abnormally high blood uric acid does not mean that the blood itself is excessively acidic.
These are normal metabolic processes.
Tony hypothesises that poor coordination of digestion, absorption, metabolism and waste handling may make these processes more consequential.
19. Third core principle: separate acid and alkaline cycles
Acid and alkaline digestive periods should be made as distinct as practical.
Tony believes abnormal overlap may create problems in a compromised digestive system.
Clear temporal separation is therefore central to the experiment.
20. Spinach observation
Very well-overcooked spinach has remained a consistent component.
It provides a large amount of vitamin K1 relative to normal adequate intake.
Tony does not know whether vitamin K1, another spinach component or coincidence explains the observation.
When spinach is removed, he reports pain and abnormal right-arm sensations returning. When spinach is restored, symptoms improve again.
This does not establish vitamin K as a treatment.
He includes the observation because it has been repeatedly reproducible for him.
21. The whole theory reduced to three central principles
The theory can be reduced to three central principles.
Dramatically reduce and stabilise intestinal-transit viscosity over a prolonged period.
Control the presentation and processing of protein using a slippery, viscosity-stabilised environment.
Create a clear temporal separation between the acid and alkaline digestive phases.
Tony
POST 2 OF 4
DEVELOPMENT OF THE LARGER THEORY
22. Old Engine Syndrome
Old Engine Syndrome is a proposed term for progressive loss of biological reserve, not simply ageing.
One system becomes slightly less efficient. Other systems compensate. Compensation increases workload elsewhere. Those compensating systems may then deteriorate.
This creates a cascade of metabolic diminishing returns.
The analogy is an ageing motor vehicle that still runs but requires increasing compensation.
Examples include poorer compression, cooling, ignition, fuel delivery and contamination of oil.
Individual defects may be small, but the combined loss of reserve becomes important.
23. One foot on the accelerator and one on the brake
Modern eating can create almost continuous metabolic activity.
Breakfast, snacks, lunch, afternoon food, dinner, alcohol, dessert and late food may overlap.
Digestive secretion, absorption, nutrient processing, hormones, liver metabolism, nitrogen handling, glucose regulation, motility and fermentation may occur in overlapping waves.
A young healthy system may tolerate this well.
An ageing or damaged system may have insufficient reserve.
The main idea is that individual processes still work, but require progressively more effort.
24. Upstream versus downstream science
The exhaust-pipe analogy distinguishes observable consequences from underlying causes.
Scientists can precisely analyse what emerges downstream while potentially missing what caused it upstream.
An engine example includes smoke, hydrocarbons, particulate matter and water vapour at the exhaust.
Upstream faults could include crankcase pressure, coolant contamination, ignition breakdown, unequal compression, incorrect fuel mixture or overheating.
Downstream abnormalities can therefore be genuine while still reflecting an earlier malfunction.
25. Application to Alzheimer’s and Parkinson’s
Amyloid-beta and tau are important in Alzheimer’s.
Alpha-synuclein is important in Parkinson’s.
Protein misfolding, aggregation, impaired clearance and cellular stress are accepted areas of neurodegenerative research.
The hypothesis does not reject these findings.
The main question is why the cellular environment increasingly allows these abnormalities to become significant.
Protein abnormalities may sometimes be downstream evidence of an upstream metabolic problem.
26. Protein-folding hypothesis
Tony is not claiming that all protein misfolding can be prevented.
Misfolding can occur during normal biology. Cells normally fold, identify, repair and remove abnormal proteins.
The hypothesis concerns the severity and consequences of protein abnormalities.
The metabolic environment may affect how damaging an existing abnormality becomes.
The analogy is that the same ignition defect produces different consequences depending on engine workload.
The goal is therefore to reduce upstream workload rather than necessarily eliminate every downstream abnormality.
The engineering principle is to reduce load, bypass inefficient pathways, remove resistance and restore reserve capacity.
27. Stop staring only at the exhaust
Downstream findings such as amyloid, tau, alpha-synuclein, oxidative injury, inflammation and mitochondrial dysfunction may all be real and important.
The argument is to investigate upstream causes simultaneously.
Using the engine analogy, inspect compression, cooling, ignition, contamination and crankcase pressure rather than looking only at exhaust products.
Ask whether a system with reduced reserve is being worked unnecessarily hard.
Old Engine Syndrome is intended to describe this progressive loss of reserve and compensatory burden.
EXISTING DIETARY CLUES THAT FIT THE THEORY
28. Three dietary clues
Three dietary approaches are considered relevant clues: the ketogenic diet, Mediterranean diet and low-FODMAP diet.
None individually proves the theory.
Each is viewed as potentially revealing a different part of the same upstream problem.
29. Ketogenic clue
Ketogenic approaches have been investigated in Alzheimer’s, mild cognitive impairment and Parkinson’s.
The evidence is interesting but incomplete.
Ketosis changes the available fuel environment. Ketone bodies can provide an alternative fuel, including for the brain.
Tony’s experiment uses MCT partly for this reason.
He is not following a conventional ketogenic diet.
He is extracting the principle of alternative fuel availability and reduced dependence on a single glucose-producing pathway.
30. Mediterranean-diet clue
Higher Mediterranean-diet adherence has been associated with lower rates of several neurological conditions.
This does not mean the diet prevents or cures Alzheimer’s or Parkinson’s.
Mediterranean foods can contain organic acids such as citric acid.
Existing research does not prove citric acid explains the observed Mediterranean-diet associations.
Tony’s idea is to isolate and deliberately manipulate citric acid and intestinal conditions.
This is presented as a testable hypothesis rather than an established finding.
31. Low-FODMAP clue
FODMAP carbohydrates may be incompletely absorbed and fermented.
They can increase intestinal water and gas.
Reducing FODMAPs can reduce bloating and gastrointestinal symptoms in susceptible people.
Gas is considered mechanically important in a narrowed, dilated or poorly coordinated intestine.
Tony therefore restricts material available for fermentation.
The later alkaline phase is also intended to lessen the consequences of trapped gas.
His approach is not literally a low-FODMAP diet.
The conceptual connection is reducing fermentable load, gas and mechanical pressure.
32. Three partial solutions combined
The ketogenic approach changes fuel supply.
The Mediterranean observation changes the dietary environment, with Tony specifically investigating organic acids.
The low-FODMAP principle reduces fermentation, gas and intestinal workload.
Tony combines selected principles rather than following any one diet.
He adds deliberate acid/alkaline separation, control of protein presentation, major manipulation of viscosity and long periods without a conventional meal.
He believes this combination has produced his results, but recognises that proper testing is required.
Tony
POST 3 OF 4
HOW THE THEORY IS CURRENTLY PUT INTO PRACTICE
33. Putting the principles into practice
The overall objectives are to maximise digestion, improve passage through the digestive tract, minimise residual waste, use nutrient-dense efficient foods and control timing carefully.
34. One main morning meal
Only one conventional substantial meal is eaten each day.
It is eaten in the morning and centred on protein, fat and nutrient density.
Solid scrambled eggs and mussels are eaten first.
The acidic viscosity-stabilised mixture follows several minutes later.
35. Why eggs, mussels, spinach and low-sodium tomato paste
These foods were chosen after experimenting with many alternatives, with the aim of achieving high nutrient density in relatively little physical food volume.
Eggs provide complete, highly bioavailable protein containing all nine essential amino acids. They are particularly valuable for choline, as well as vitamin B12, riboflavin, selenium, phosphorus, iodine and fat-soluble vitamins.
Egg yolks also provide phospholipids and essential fatty acids, while supplying much of the egg’s choline and micronutrient content.
Mussels provide complete protein with an exceptionally concentrated micronutrient profile, particularly vitamin B12, iron, selenium, manganese, zinc and copper.
They also provide long-chain marine omega-3 fatty acids EPA and DHA.
The combination of eggs and mussels therefore provides high-quality protein together with nutrients involved in red-blood-cell production, neurological function, energy metabolism, antioxidant defence and tissue maintenance.
Cooked spinach provides a concentrated source of vitamin K1, folate, provitamin-A carotenoids and minerals including magnesium and potassium.
Low-sodium tomato paste provides concentrated potassium together with carotenoids, particularly lycopene, and smaller amounts of several other vitamins and minerals without unnecessarily increasing sodium.
Spinach and tomato paste therefore contribute importantly to the mineral and electrolyte profile, particularly potassium and magnesium, while substantially broadening the micronutrient range of the meal.
Together, eggs, mussels, spinach and low-sodium tomato paste are intended to provide a broad spectrum of essential amino acids, vitamins, minerals, electrolytes and essential fats from a relatively small quantity of food.
The aim is nutritional efficiency rather than food volume.
This does not claim that the combination, by itself, meets every nutritional requirement.
36. Enjoyment of the morning meal
The single substantial meal should still feel like real food.
Scrambled eggs make breakfast enjoyable rather than purely clinical.
Tony considers this psychologically important for maintaining the routine.
37. Scrambled-egg meal
The scrambled-egg meal consists of two eggs, a small amount of milk and approximately 20 peeled, cooked mussels.
It is eaten before the acidic mixture.
38. Handling fats
Tony avoids freely available liquid fat as a separate drink or loose oil.
Oils are incorporated into the viscosity-stabilised mixture.
Other fats are naturally present in eggs.
Egg yolks contain phospholipids including phosphatidylcholine with emulsifying properties.
The scrambled eggs and acidic mixture remain separate rather than being mixed together.
39. Morning viscosity-stabilised acidic mixture
The morning mixture contains half a cup of very well-cooked spinach, one heaped tablespoon of very-low-sodium tomato paste, approximately 0.5 g xanthan gum, half a standard scoop of PEG 3350/OsmoLax, two full-sized scoops of citric acid totalling approximately 40 g, one dessert spoon of olive oil and one dessert spoon of MCT oil.
It is mixed thoroughly for several minutes until maximum viscosity is reached.
It is consumed separately several minutes after breakfast.
40. Reason for meal order
Tony hypothesises that solid food first and the viscous mixture second influence the mixing and organisation of stomach contents near the pylorus.
He wonders whether the later viscous mixture allows the acidic component to mix more thoroughly with the meal before emptying.
He does not claim the mixture forms a literal plug or mechanically blocks the pylorus.
Gastric mixing and emptying are physiologically complex.
This remains a working hypothesis based on personal observations.
41. Acid cycle
The morning meal and acidic mixture form the acid phase.
No further conventional meal occurs until the next morning.
42. Between the cycles
There is no second conventional meal and the chocolate mousse is eaten only as required.
The mousse is made from cream, cocoa powder, icing sugar and MCT oil.
In practice, hunger is generally absent. The mousse is available as a small, energy-dense food rather than another full meal.
The icing sugar provides carbohydrate that is digested and absorbed as glucose, while the cream and cocoa contribute additional energy and nutrients.
MCT oil is rapidly absorbed and transported to the liver, where medium-chain fatty acids can be converted into ketone bodies.
These ketones can cross the blood-brain barrier and provide the brain with an alternative energy substrate alongside glucose.
The intention is therefore not to eliminate glucose, but to maintain metabolic flexibility by providing both glucose and the potential for ketone production, so the brain has more than one available energy source.
The overall purpose is to maintain energy availability between cycles without introducing the volume and complexity of another conventional meal.
43. Alkaline cycle
The alkaline cycle begins at approximately 1:00 pm, after the morning acidic digestive cycle has been allowed to run its course.
One or two Quick-Eze Original tablets are dissolved in water and consumed as part of the alkaline cycle.
Quick-Eze contains the alkaline antacids calcium carbonate, magnesium carbonate and magnesium trisilicate, which neutralise gastric acid.
Although the manufacturer’s adult maximum is 12 tablets in 24 hours, this regimen deliberately limits intake to no more than four tablets per day.
This conservative limit recognises that the tablets provide appreciable quantities of calcium- and magnesium-containing compounds, and that regular long-term antacid use warrants considerably more caution than occasional use.
The manufacturer recommends medical advice when antacids are required frequently.
A degassing tablet is often used during this period when required.
This is followed by peppermint tea.
The alkaline sequence is generally performed twice, with the final cycle approximately two hours before breakfast.
The term “alkaline cycle” describes the digestive regimen and does not imply that the body’s blood pH is being deliberately made alkaline.
The final alkaline drink occurs before returning to the next morning’s acid phase.
44. Subjective alkaline-phase effect
Tony describes a very large sensation of digestive relief.
It feels as if the effect progresses through the digestive tract and releases pressure.
He calls this the “alkaline effect.”
He cannot prove an alkaline solution is literally progressing through the bowel in the way it feels.
He cannot determine whether the relief comes from acid neutralisation, gas movement, motility, peppermint, antacid effects or a combination.
The consistency of the sensation made this phase important to the experiment.
45. Safety qualification around the alkaline regimen
This is a description of Tony’s personal experimental regimen rather than a recommended dosing schedule.
Antacid products contain active mineral salts.
Repeated use can contribute appreciable quantities of calcium, magnesium and other compounds.
Different degassing products contain different active ingredients.
Repeated or long-term antacid use cannot automatically be assumed appropriate or safe for another person.
The quantities and frequency used in this experiment should therefore be distinguished from general medical recommendations.
Tony
POST 4 OF 4
WHAT THE ENTIRE ROUTINE IS TRYING TO ACHIEVE
46. What the protocol is trying to compensate for
Tony believes he is manually compensating for digestive regulatory functions that are no longer adequate.
Possible contributors include ageing, longstanding intestinal damage, abnormal anatomy, impaired motility or a combination of these.
His own structural abnormality may require ongoing compensation.
This may differ substantially from someone with normal anatomy.
47. Long-term hypothesis
Alzheimer’s and Parkinson’s generally develop progressively.
If chronic upstream digestive/metabolic dysfunction contributes, years of dysfunction might require prolonged reduction of workload rather than a rapid intervention.
The core strategy is to reduce the difficulty of intestinal transit, reduce digestive workload, control protein presentation, use nutrient-dense food with low volume, separate acid and alkaline phases, and provide later energy without another meal.
The hypothesis is that prolonged lower physiological workload provides greater reserve.
48. Potential temporary versus permanent intervention
Tony cannot establish that the approach reverses Alzheimer’s or Parkinson’s pathology.
If the concept proved correct, people with otherwise normal gastrointestinal anatomy might not require such intensive intervention permanently.
Tony believes his own abnormal anatomy may make continuing compensation necessary.
He does not propose that normal digestive systems require lifelong manual control of acid and alkaline phases.
49. Underlying research question
What happens when the digestive system gradually loses its ability to regulate these processes autonomously?
What secondary effects occur elsewhere in the body if this continues for years?
CITRIC-ACID REGULATORY AND SAFETY CONTEXT
50. FDA regulatory position on citric acid
Citric acid is naturally occurring in plant and animal tissues.
It participates in normal human metabolism.
The FDA has affirmed citric acid as GRAS — Generally Recognized As Safe — for direct food use.
The cited regulation is 21 CFR §184.1033.
Food use is governed by current good manufacturing practice.
The FDA does not specify a numerical maximum daily intake in that regulation.
Lack of a numerical limit does not mean unlimited amounts are safe.
GRAS status does not establish the safety of experimental 40 g, 75 g, 100 g or other very high daily doses.
GRAS food use is not equivalent to approval of a therapeutic high-dose regimen.
51. Historical regulatory assessment
Citric acid was evaluated by the Select Committee on GRAS Substances.
FDA records the 1977 SCOGS evaluation.
Citric acid and various citrate compounds were subsequently affirmed as GRAS direct human food ingredients.
52. JECFA position
The Joint FAO/WHO Expert Committee on Food Additives evaluated citric acid and several citrate salts.
It assigned an Acceptable Daily Intake described as “not limited.”
This means a conventional numerical ADI was not considered necessary for normal food-additive use.
It does not mean any quantity can be consumed indefinitely without risk.
53. Qualification regarding Tony’s citric-acid exposure
Tony’s personal intake was generally approximately 75–100 g daily for more than six months.
This is much greater than ordinary dietary exposure.
It is reported as part of the experiment, not as a safe recommended dose.
FDA GRAS status and JECFA classification do not prove chronic intake at this level is safe.
54. Dental erosion
Citric acid can demineralise dental enamel.
Evidence for erosion and enamel softening is substantially clearer than many of the proposed systemic effects.
Tony no longer considers it scientifically appropriate to describe even 40 g/day as insignificant.
Chronic safety at such amounts has not been established.
Repeated contact of acidic liquid with teeth poses a credible erosion risk.
Measures mentioned include minimising tooth contact, using a straw towards the back of the mouth, rinsing with water afterwards and avoiding immediate brushing.
These precautions reduce exposure but cannot guarantee protection.
55. Established versus unestablished citric-acid claims
It is established that citric acid is GRAS for food use.
It is established that JECFA did not assign a conventional numerical ADI.
It is established that citric acid can erode dental enamel.
It is a personal observation that Tony consumed approximately 75–100 g/day for more than six months.
It is a personal observation that his blood tests improved.
It is not established that this high chronic dose is safe.
It is not established that citric acid caused the blood-test improvement.
It is not established that other people would respond similarly.
WHERE THE HYPOTHESIS NOW STANDS
56. Potential wider implications
Tony believes the hypothesis could potentially extend beyond Alzheimer’s and Parkinson’s if the proposed mechanism were eventually demonstrated.
He recognises the scale of this proposition.
Personal experience is not scientific proof.
The observations have produced a hypothesis in which he has strong confidence.
He believes it should be scientifically investigated rather than dismissed simply because it differs from conventional explanations.
57. Three possible outcomes
Tony sees three possible outcomes.
The theory is substantially right and eventually recognised.
The theory is wrong and Tony accepts being publicly proven wrong.
The experiment itself could produce an unexpected or harmful result.
Strong conviction is presented as necessary to pursue an unconventional hypothesis.
The preference is for qualified scientists to investigate the idea properly.